·
Ibogaine and the Heart: QT Prolongation
Ibogaine blocks a potassium channel that resets the heartbeat. What that does to the QT interval, who it has killed, and what screening can and cannot catch.

Ibogaine blocks the hERG potassium channel, which lengthens the QT interval on an electrocardiogram and can allow a fatal arrhythmia, torsade de pointes, to begin. The risk outlasts the psychoactive effects: published deaths occurred between 1.5 and 76 hours after the dose. Screening measures that risk; it does not remove it.
Ibogaine’s danger is not that it is a powerful hallucinogen. It is that it interferes with the electrical system of the heart, and it does so for far longer than the psychoactive effects last. Most of the harm ibogaine has caused runs through this mechanism, usually in combination with pre-existing disease or other drugs.
What ibogaine does to a heartbeat
Each heartbeat is an electrical event. Cells depolarise to contract, then repolarise to reset before the next beat. The resetting phase depends on potassium leaving the cell, and one of the main channels carrying that current is called hERG.
Ibogaine inhibits hERG at low micromolar concentrations, which is to say at concentrations reached in ordinary use rather than in overdose. Block the channel and repolarisation slows. The cell takes longer to reset, the action potential lengthens, and on an electrocardiogram the interval between the Q and T waves stretches. That is the QT interval, and corrected for heart rate it is written QTc.
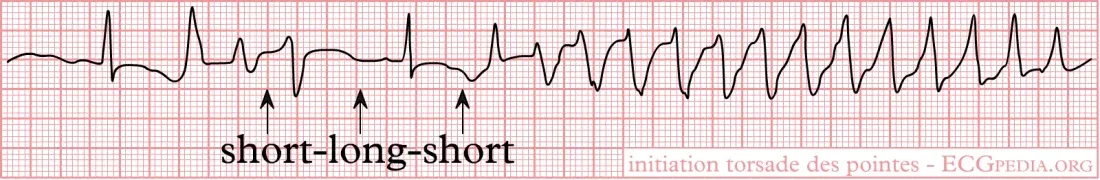
A long QTc is not itself a symptom. Nobody feels it. What it means is that the heart spends longer in a vulnerable state, during which an ordinary early beat can land at the wrong moment and start a polymorphic ventricular rhythm called torsade de pointes. Torsade sometimes stops on its own. Sometimes it degenerates into ventricular fibrillation, and then the heart stops pumping.
Two features make this worse in ibogaine’s case. The first is duration: in the fatality series, deaths occurred between 1.5 and 76 hours after the dose, well past the point where a person seems to have come through the difficult part. Why the window is that long is not settled. Noribogaine, the active metabolite, persists far longer than ibogaine and is often named as the reason, but in a 2024 study of fourteen patients the QTc change tracked ibogaine concentrations and not noribogaine’s, and the authors concluded that the cardiac effect is most likely driven more by ibogaine itself. A study that small cannot close the question either way. The second is that the drug also slows the heart rate, and a slower rate lengthens the QT interval further.
Someone who has finished the visionary phase and is resting has not passed the risk. Deaths in the published series occurred as late as 76 hours after the dose, long after the acute effects had ended, which is the argument for monitoring that continues overnight rather than ending when the person stops talking.

Who has died, and what they had in common
The most systematic count reviewed all available autopsy, toxicological and investigative reports for every known death outside West Central Africa between 1990 and 2008. It found nineteen people, fifteen men and four women aged 24 to 54.
The pattern in those deaths matters as much as the count. Postmortem evidence did not show a characteristic syndrome of neurotoxicity. In 12 of the 14 cases with adequate data, advanced pre-existing conditions, mainly cardiovascular, or other commonly abused substances explained or contributed to the death. Withdrawal seizures from alcohol and benzodiazepines, and use of raw plant preparations of unknown strength, appeared as further risk factors. The wider record, and what it does and does not license anyone to conclude, is on is iboga safe.
A second pattern runs through the case reports. Where potassium was measured in ibogaine-associated fatalities and arrhythmias, it was low. Hypokalaemia lengthens the QT interval on its own, and it is common in people who are vomiting, in withdrawal, drinking heavily or poorly nourished, which describes a large share of those seeking ibogaine. It is also correctable in an afternoon.
Why a clean history is not a clearance
It would be convenient if the risk were confined to people with known heart disease. It is not. A 2026 review in Addiction states that the arrhythmias occur at therapeutic doses and in individuals without pre-existing cardiac conditions.
The same review points at a likely reason. Ibogaine is metabolised by the enzyme CYP2D6, and CYP2D6 activity varies enormously between people for genetic reasons. A poor metaboliser clears the drug slowly, holds a higher concentration for longer, and is exposed to more hERG blockade from the same amount. The review recommends CYP2D6 genotyping before treatment alongside cardiovascular monitoring. It is rarely offered, and its absence is a reasonable thing to ask about.
This is the point where the reassuring version of this subject and the accurate version part company. Screening removes the risks that can be measured. It does not remove a risk carried in someone’s genotype and not tested for.
What the material itself contributes
Cardiac risk is not only a property of the molecule. It is also a property of what someone actually swallowed.
A ten-year case series from the United Kingdom National Poisons Information Service illustrates this. Of seven patients, six showed features of cardiotoxicity, including cardiac arrest, torsade de pointes, QT prolongation and bradycardia. The reported sources were an online purchase, a dealer, and in two cases a shaman. Most had taken root bark rather than a purified preparation, and the quantities reported varied by nearly sevenfold between cases. Where that material comes from, and what each country permits, are separate questions: see legal status by country.
That spread is the finding. With raw bark, alkaloid content is not fixed, so the same weight can deliver very different amounts of drug. Nobody in that series had a verified alkaloid content, and the material is discussed further on buying iboga online.
What screening is meant to catch
A responsible pre-treatment assessment is not a formality, and its components map onto specific risks rather than onto a checklist.
| What is done | What it is for |
|---|---|
| Baseline ECG with calculated QTc | Establishes the starting interval and can reveal congenital long QT, which a normal resting trace does not rule out |
| Potassium and magnesium, corrected before dosing | Removes an amplifier of QT prolongation present in every case report where potassium was measured |
| Full medication and substance history | Identifies other QT-prolonging drugs, methadone above all; the rest are listed under ibogaine side effects |
| Liver function tests | Impaired clearance means higher and longer exposure |
| Continuous cardiac monitoring through and after the acute phase | Detects the arrhythmia in the window where it actually occurs |
| Resuscitation equipment and staff competent to use it | Torsade is survivable if treated within minutes |
That second row carries a caveat worth stating, because it is the one most often oversold. Congenital long QT syndrome is frequently concealed. In a study of genotyped families, only a quarter of gene carriers showed the condition clinically at all, and conventional diagnostic criteria correctly identified just 38 per cent of them. A third of the relatives judged unaffected on clinical grounds turned out to carry the mutation.
A clean ECG lowers the estimate of risk. It does not clear a person.
Two absences are worth noticing when assessing a provider. CYP2D6 genotyping is recommended in the recent literature and is rarely offered. And a “medically supervised” description says nothing about whether monitoring continues through the night, which is when the published deaths occurred.
The counter-evidence
In 2024 a Stanford group reported outcomes for 30 veterans given ibogaine together with intravenous magnesium, magnesium having been chosen specifically because it shortens the QT interval. No serious cardiac events occurred.
The result deserves to be reported and deserves not to be inflated. The authors state that it was not a randomised controlled trial and that participants had arranged the treatment themselves, on a grant from a veterans’ charity, before researchers were involved. A group healthy enough and organised enough to travel abroad is not the group that appears in a fatality series. What the study supports is that screened, monitored, magnesium-supplemented administration produced no cardiac events in 30 people. What it does not support is a claim that the cardiac problem has been solved.
What is still unknown
The rate is unknown. Nineteen deaths between 1990 and 2008 is a numerator without a denominator, because nobody knows how many people took ibogaine in that period.
The threshold is unknown. There is no established QTc value above which ibogaine is agreed to be unsafe and below which it is agreed to be acceptable. Providers use cut-offs; those cut-offs are house practice rather than validated limits.
The contribution of each measure is unknown. Magnesium, electrolyte correction and monitoring are given together, and no trial has separated them. It is reasonable to think screening helps. It is not established how much, or which part does the work.
Common questions
Sources
7 sources · How we source
- The pharmacokinetics and pharmacodynamics of ibogaine in opioid use disorder patients
- The Anti-Addiction Drug Ibogaine and the Heart: A Delicate Relation
- Rare but relevant: Ibogaine and cardiovascular complications, prolonged QT interval and ventricular arrhythmias
- Fatalities temporally associated with the ingestion of ibogaine
- A case series of ibogaine toxicity reported to the UK National Poisons Information Service over a 10-year period
- Low penetrance in the long-QT syndrome: clinical impact
- Magnesium-ibogaine therapy in veterans with traumatic brain injuries